
How Is Plantar Fasciitis Diagnosed? What to Expect at Your Appointment
When your heel hurts every morning, it's tempting to search for one clear answer. Maybe it's plantar fasciitis. Maybe it's a heel spur. Or maybe the pain started after a long week on your feet and you can't tell what changed. The uncertainty can be almost as frustrating as the pain itself, especially when you're wondering whether you need an X-ray or an expensive specialist visit.
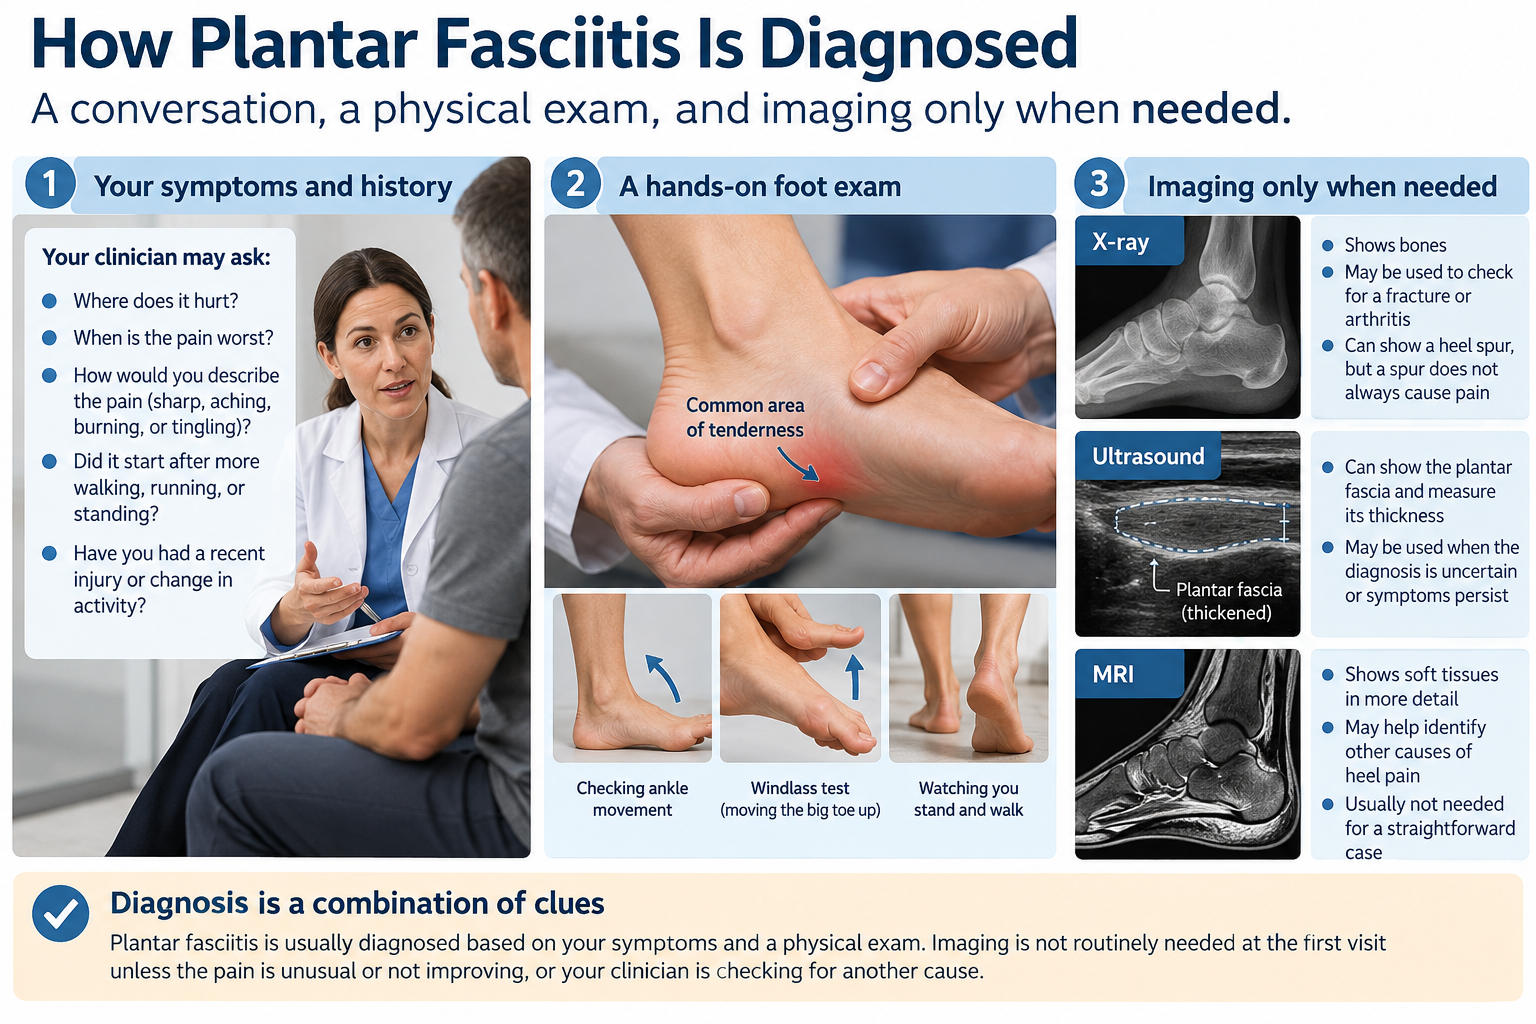
Here's the reassuring part: plantar fasciitis is usually diagnosed through your symptoms and a hands-on examination, without an MRI or other scan. The clinician wants to understand where your heel hurts, when it hurts most, and whether the findings fit a plantar fascia problem or point toward something else. The American Academy of Orthopaedic Surgeons (AAOS) describes this history-and-examination approach, with additional testing when another cause needs to be considered.
Knowing what the appointment involves can make the process less intimidating. It also helps you ask better questions and understand why a test may—or may not—be worth doing.
How Doctors Recognize the Pattern of Plantar Fasciitis
Imagine two people who both say, “My heel hurts.” One feels a sharp jab under the inner part of the heel when stepping out of bed. After a few minutes of walking, the pain settles, though it returns after a long shift. The other has burning pain and tingling that travels across the foot, even while resting. Both deserve attention, but they don't tell the same story.
The first pattern is typical of plantar fasciitis. Pain is often concentrated beneath the heel, especially near the inner side, and the first steps after sleep or a period of sitting can be the worst. The 2023 heel pain clinical practice guideline includes this first-step pain pattern among the findings clinicians use when evaluating plantar heel pain.
Your clinician will ask more than whether the heel hurts in the morning. They'll want to know when it began, whether it came on gradually or after an injury, and how your routine has changed. Did you start walking longer distances? Return to running? Take a job that requires standing on hard floors? Does the pain ease with movement, or build steadily as the day goes on?
These questions aren't small talk. They help distinguish a familiar plantar fascia pattern from problems that may need a different examination or treatment. The location and timing of pain provide clues, not a diagnosis on their own.
What Happens During a Plantar Fasciitis Foot Exam?
You generally won't need to do anything complicated. The clinician may ask you to remove your shoes and socks, point to the most painful spot, and stand or walk a short distance. Then they'll examine the foot and ankle while checking whether the tenderness matches your description.
For plantar fasciitis, the most sensitive area is often near where the plantar fascia attaches to the heel bone. Pressing there may reproduce the pain you've been feeling. The clinician may also check how far your ankle bends upward, look at foot movement, and gently move your toes to see how the tissue responds. These are among the examination findings discussed by AAOS.
One maneuver you might hear about is the windlass test. Moving the big toe upward puts tension through the plantar fascia. If that recreates familiar heel pain, it can add to the overall picture. But a positive or negative result doesn't settle the diagnosis by itself. The 2023 clinical guideline emphasizes interpreting examination findings alongside the history and symptom pattern.
Just as important is what the clinician finds outside the expected pattern. Pain mainly behind the heel, unusual swelling, numbness, or tenderness that seems centered in the heel bone may lead the examination in another direction. A good visit isn't about making every symptom fit plantar fasciitis; it's about checking whether plantar fasciitis really is the best explanation.
Do You Need an X-Ray to Diagnose Plantar Fasciitis?
Often, no. If your symptoms and examination are typical, imaging may not change the initial plan. Mayo Clinic explains that the diagnosis is commonly made from medical history and physical examination alone.
That can feel surprising when the pain is severe. But an X-ray primarily shows bones, not the plantar fascia itself. Its value is often in checking for another possible cause, such as a fracture or a bone-related problem, when the history or examination raises that concern.
An X-ray can also show a heel spur. The word spur sounds as if something sharp must be digging into your foot, but that isn't how the finding should be interpreted. Heel spurs can be present without pain, and seeing one doesn't prove it's causing your symptoms. AAOS discusses this distinction.
So if your clinician says you don't need an X-ray, that isn't necessarily a sign they're overlooking something. And if they recommend one, it's reasonable to ask what other condition they're trying to rule out.
When Ultrasound or MRI May Be Helpful
Ultrasound and MRI can show soft tissues in more detail than a standard X-ray. Ultrasound may reveal changes in plantar fascia thickness or appearance, while MRI can help evaluate the fascia and certain other injuries. Still, neither test is automatically necessary just because your heel hurts.
Consider someone whose pain follows the classic morning pattern and whose examination fits plantar fasciitis. A scan may add little to the initial decision. Now consider someone whose pain started after a sharp increase in running, doesn't behave like typical first-step pain, and remains difficult to explain on examination. In that situation, imaging may help investigate a stress injury or another diagnosis.
Persistent symptoms can also change the conversation. If you've followed a reasonable care plan and the heel isn't improving as expected, the clinician may revisit the original diagnosis and decide whether further testing would be useful. The 2023 clinical practice guideline addresses reassessment when findings do not fit the usual presentation or progress is limited.
A useful question at any stage is: “What would this scan tell us, and how would the result change my care?” That keeps the discussion focused on what helps you rather than testing for its own sake.
What Else Might Your Clinician Check for?
Heel pain doesn't all come from the same tissue. A clinician may consider other causes when your symptoms or examination don't fit plantar fasciitis.
For example, pain at the back of the heel may involve the Achilles tendon. A heel bone stress injury becomes more concerning when pain follows a substantial increase in impact activity and the examination suggests bone tenderness. Burning, tingling, or numbness may point toward nerve irritation. Pain centered directly under the heel, especially with pressure on hard surfaces, may suggest a problem involving the heel's cushioning fat pad.
These distinctions aren't meant to help you diagnose yourself from a list. They explain why a clinician asks detailed questions and examines more than one spot. The 2023 guideline specifically calls for considering alternative diagnoses when the presentation doesn't match typical plantar heel pain.
For a fuller explanation of how those conditions differ, our separate article on heel pain causes can help once its final URL is published and verified. The job of this page is to explain the diagnostic process, not to turn you into your own examiner.
When Should You Schedule an Appointment for Heel Pain?
If heel pain keeps returning, gets worse, interferes with normal walking, or hasn't improved after about two weeks of reasonable self-care, arranging an appointment makes sense. You should also get assessed for tingling or loss of feeling, and people with diabetes should not assume new foot pain is routine plantar fasciitis. These are among the reasons for seeking medical advice in the NHS plantar fasciitis guidance.
Some situations need faster attention. Severe pain after an injury, an obviously deformed foot, inability to bear weight, or marked redness and swelling with fever should not wait for a routine plantar fasciitis appointment. Those symptoms can point to a different and potentially urgent problem.
If you're unsure which type of appointment you need, describe the symptoms when contacting your healthcare provider. You don't have to decide the diagnosis before asking for help.
How to Prepare for Your Plantar Fasciitis Appointment
You don't need a detailed spreadsheet of every painful step. A few useful observations are enough: where the pain sits, when it began, whether the first steps after rest are worst, what activities bring it on, and what you've already tried. If your routine changed around the time the pain started, mention that too.
It can help to bring the shoes you wear most often, especially if you spend long hours standing or have questions about fit. But don't feel you need to buy special footwear before the visit. Your existing shoes and your description of daily activities give the clinician more useful context than a brand-new pair chosen on a guess.
Think about what you need to get back to doing. A runner hoping to return to training and a nurse struggling through twelve-hour shifts may have similar heel pain but very different practical challenges. Explaining those goals helps turn the diagnosis into a plan you can actually follow.
What Happens After Plantar Fasciitis Is Diagnosed?
A diagnosis should lead to a clear explanation and a reasonable starting plan, not an automatic shopping list. Depending on your symptoms, that plan may involve adjusting aggravating activity, plantar fascia and calf stretching, progressive strengthening, and discussion of footwear or other supports. The 2023 physical therapy guideline outlines evidence-based approaches to managing plantar heel pain.
Custom orthotics, injections, scans, and surgery aren't inevitable next steps. In fact, understanding why your clinician thinks plantar fasciitis is the likely cause should make it easier to evaluate which treatments are worth trying and which may be unnecessary.
If the pain doesn't respond as expected, that isn't a reason to blame yourself or simply keep buying products. It may be time to revisit the activity plan, check whether the original diagnosis still fits, or consider other explanations.
Common Questions About Plantar Fasciitis Diagnosis
Can I Tell Whether I Have Plantar Fasciitis at Home?
Does a Heel Spur Confirm Plantar Fasciitis?
Can Plantar Fasciitis Be Diagnosed Without an MRI?
What If My Heel Pain Doesn't Improve After Treatment?
What You Should Understand Before Leaving the Appointment
The best outcome isn't simply hearing the words plantar fasciitis. It's understanding why the clinician thinks that diagnosis fits your symptoms, what other problems have been considered, and what your next steps should be.
You should know what to try first, what kind of improvement to watch for, and when to come back if the plan isn't helping. That gives you something more useful than a scan result alone: a clear explanation of your heel pain and a sensible path forward.