
Night Splints for Plantar Fasciitis: What the Evidence Says
If plantar fasciitis has made your first steps out of bed miserable, the idea of treating your heel while you sleep can sound appealing. You put on a night splint, go to bed, and hope that tomorrow morning will be easier. But sleeping with your foot held in an unfamiliar position is a bigger commitment than slipping an insole into a shoe. Before buying one, it's worth understanding what a night splint is supposed to accomplish, what the research actually says, and whether your particular pain pattern makes it a reasonable option.
Night splints are most relevant when plantar fasciitis causes persistent pain with the first steps after sleep. They are not an essential purchase for everyone with heel pain, and they do not replace stretching, sensible activity changes, or a diagnosis that fits your symptoms. The 2023 plantar heel pain clinical practice guideline specifically recommends a one- to three-month night-splint program for people with plantar fasciitis who consistently have first-step morning pain. The details behind that recommendation matter, though, especially if you're deciding whether the discomfort and cost are worthwhile.
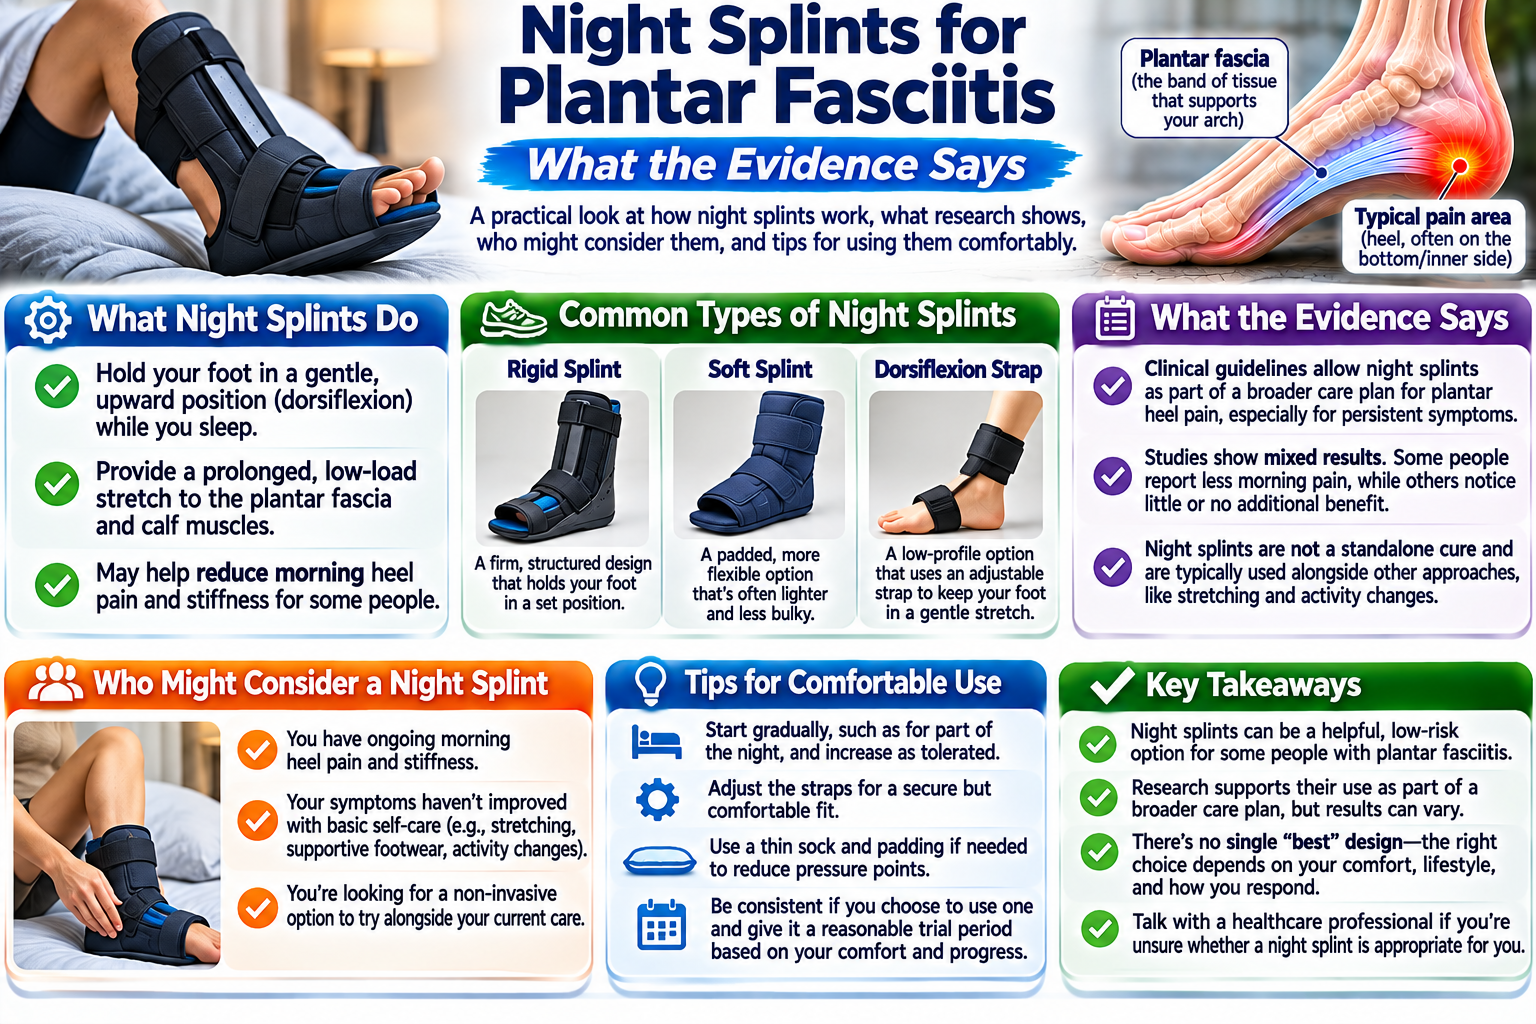
Why Morning Heel Pain Is the Reason Night Splints Exist
Imagine that you can walk through most of the afternoon reasonably well, but getting up in the morning feels like stepping on a sharp object. After a few minutes, the pain settles enough for you to get on with your day. Then the same thing happens after you've been sitting for a long time. This familiar start-up pattern is common in plantar fasciitis, although it doesn't confirm the diagnosis by itself. The American Academy of Orthopaedic Surgeons (AAOS) describes first-step pain after rest as a typical symptom.
When you sleep, your ankle often rests with the toes pointing somewhat downward. A night splint is designed to limit that position, usually holding the ankle closer to neutral or gently upward. Some designs also position the toes. The goal is to maintain a gentle stretch through the calf–plantar fascia system rather than asking a sensitive heel to move abruptly from rest to full weight-bearing when you stand.
That explanation describes the device's intended function, not proof that the plantar fascia tears overnight or that splinting repairs tissue while you sleep. The precise causes of morning pain are more complicated than those popular explanations suggest. A splint is an attempt to make the first steps more comfortable; it isn't a way to confirm what's causing the pain.
What the Evidence Says About Night Splints for Plantar Fasciitis
The most useful starting point is the 2023 clinical practice guideline published in the Journal of Orthopaedic & Sports Physical Therapy. Its recommendation is specific: clinicians should prescribe a one- to three-month night-splint program for people with plantar fasciitis who consistently experience pain with their first steps in the morning.
That sounds decisive, but there is a qualification worth knowing. The 2023 guideline states that its evidence update identified no new studies investigating night-splint effectiveness, so the recommendation was carried forward from the 2014 guideline. In other words, this is an established clinical recommendation, not a claim that a new wave of high-quality trials has proven night splints work for everyone. The guideline publisher's page identifies the current revision and its authors.
Other established medical references also include night splints among nonsurgical treatment options. AAOS discusses them for morning heel pain, while MedlinePlus lists splinting alongside stretching, footwear, and other conservative measures. These sources support considering the treatment, but they do not give you a reliable personal probability of success.
The practical interpretation is straightforward: night splints are a reasonable option to discuss for a fairly specific symptom pattern. They are not a guaranteed cure, and they shouldn't be the first purchase simply because a product description promises relief by morning.
Who May Have the Most Reason to Try a Night Splint?
Think about which part of the day is actually causing you trouble. If the first steps after waking are consistently your worst moments, and that pattern continues despite a manageable stretching and activity plan, a night splint addresses a problem you can clearly identify. It may be especially worth discussing if those painful first steps disrupt your morning routine even while other parts of the day have become more comfortable.
Now consider someone whose heel mainly hurts after an eight-hour shift or progressively worsens during long walks. That person may still have plantar fasciitis, but a device worn overnight does not directly address every daytime load that aggravates the foot. The broader plan—activity management, stretching, strengthening, and footwear comfort—may deserve more attention than another device.
The distinction matters because people often buy products based on the diagnosis printed on the package instead of the symptom they need help managing. A night splint is not inherently better because your heel pain has lasted several months. Its usefulness depends partly on whether first-step pain remains a prominent problem and whether you can actually tolerate wearing it.
If you're uncertain whether the symptoms fit plantar fasciitis at all, start with our plantar fasciitis overview before making a purchase. Pain behind the heel, numbness, significant swelling, or steadily worsening weight-bearing pain can call for a different evaluation.
Different Night Splint Designs and Their Tradeoffs
Night splints are not all built the same way. The familiar rigid boot-style design uses a shell and straps to position the foot and ankle. It may provide a more structured hold, but it can also feel bulky under the covers, especially if you move frequently in your sleep. A device that looks supportive in a product photo may be difficult to live with for several hours at a time.
Softer sock-style designs typically use fabric and a strap to pull the toes or forefoot upward. They may feel less cumbersome, but the amount and location of tension differ from a rigid ankle splint. Don't assume that every soft design reproduces the same positioning or has equivalent clinical evidence. The important questions are what the device actually holds, whether the position is tolerable, and whether it fits as intended.
Some products sit along the front of the lower leg and foot rather than enclosing the back of the ankle. These can change where straps and padding contact the skin, but a different shape doesn't automatically mean better results. Product design, fit, and personal comfort all matter, and the 2023 guideline's recommendation should not be read as an endorsement of a particular brand or construction.
For this educational article, the important comparison is between structured positioning, comfort, and the ability to use the device consistently. Our separate night-splint comparison guide can address specific product features and buying choices without turning this evidence discussion into a shopping roundup.
Why Sleep Comfort Is Part of the Decision
A treatment that interrupts sleep every night creates its own problem. You may find the splint awkward when changing positions, too warm, or irritating where a strap touches your skin. Someone who shares a bed, gets up frequently at night, or already struggles with sleep may reasonably place more weight on those inconveniences.
A splint should hold the foot gently, not force it into a painful stretch. Follow the device's fitting instructions and any clinician guidance. If it causes numbness, tingling, marked pressure, skin irritation, or increasing pain, remove it and seek advice rather than tightening or forcing the position. People with reduced foot sensation, circulation concerns, wounds, or diabetes should get individualized guidance before using a device that applies prolonged pressure.
Also consider nighttime mobility. A bulky splint may not be safe to walk in, and even a design marketed as walkable can change your balance. Follow the manufacturer's instructions about getting out of bed, and don't assume that a sleeping device is suitable for walking to the bathroom.
Comfort is not a minor luxury here. If a splint is so disruptive that you stop wearing it after two nights, the theoretical benefit won't matter much. That is a legitimate reason to discuss alternatives rather than feeling that you failed the treatment.
How Long Should You Try a Night Splint?
The 2023 clinical guideline recommends a one- to three-month program for consistent first-step pain. This is a recommended treatment window, not a promise that every person will improve within a particular number of nights. It also doesn't mean you should continue wearing a painful or poorly fitting device for months without reassessment.
If you and your clinician decide to try one, agree on what improvement would actually look like. You might notice that the first steps are less painful, that the discomfort settles sooner, or that mornings interfere less with getting ready for work. Compare similar mornings over time instead of treating one good day as proof of success.
At the same time, keep the rest of your care reasonably consistent so you can interpret changes. If you introduce a night splint, new shoes, three exercises, and a different walking schedule on the same day, you may never know what helped. Night splinting is usually best understood as one possible part of a broader plan, not a stand-alone solution.
What to Try Before Spending Money on a Night Splint
If your symptoms are mild and already improving, you may not need another product. A gentle plantar fascia stretch before standing, comfortable footwear on hard floors, and adjustments to activities that repeatedly aggravate your heel are sensible places to begin. The NHS plantar fasciitis guidance recommends supportive footwear, appropriate gentle exercises, and avoiding activities that clearly worsen symptoms.
Stretching and strengthening deserve particular attention because they help address how the foot and ankle function throughout the day, not just during sleep. The 2023 guideline recommends plantar fascia and calf stretching and foot and ankle resistance exercise as parts of care. A night splint may complement those measures for persistent morning pain, but it doesn't replace them.
It's also reasonable to consider what your current routine already accomplishes. If a few gentle stretches and the shoes you own make mornings manageable, a bulky device may add little practical value. On the other hand, if you are following a reasonable plan and first-step pain remains a major obstacle, discussing a splint is more justified than buying yet another insole without a clear purpose.
When a Night Splint Is Not the Right Next Step
Don't let a familiar symptom label override a concerning change. Heel pain that began after an injury, makes it difficult to bear weight, or is accompanied by major swelling should be assessed rather than managed with a sleeping device. Burning, numbness, or unusual pain locations can also point toward something other than typical plantar fasciitis.
The NHS advises medical assessment when foot pain is severe, worsening, recurring, or not improving after about two weeks of self-care, and for tingling or loss of sensation. People with diabetes and foot pain should also seek medical advice. A hot, markedly swollen foot with fever, or severe pain after a significant injury, warrants prompt assessment.
A splint can be a reasonable addition to a treatment plan once the diagnosis and symptom pattern make sense. It should not become a way to postpone an examination when the situation is changing or concerning.
Common Questions About Night Splints for Plantar Fasciitis
Do night splints actually work for plantar fasciitis?
Should everyone with plantar fasciitis wear a night splint?
Are soft night-splint socks as effective as rigid boots?
Can a night splint make heel pain worse?
How soon should I notice improvement?
Can I use a night splint instead of stretching or strengthening?
The Bottom Line on Night Splints and Morning Heel Pain
Night splints are worth understanding, but they aren't something every person with plantar fasciitis needs to buy. Their clearest role is in persistent first-step pain—the kind that makes getting out of bed consistently difficult even while you work on a broader recovery plan. The clinical guideline supports considering them for that situation, while the evidence update reminds us not to promise more certainty than the research provides.
If your mornings are already getting easier, you may be better served by continuing a manageable routine. If the first steps remain a major problem, a well-fitted, tolerable night splint may be worth discussing with a clinician. The goal is not to sleep in the most elaborate device. It's to make mornings and everyday movement more comfortable without creating unnecessary cost, discomfort, or lost sleep.